Detransition 5

Contrary to my usual practice I cannot link a PDF here. Below is the on-line link to the paper. It is open access but download and print are disabled.

Paper on detransition

Some of you may be familiar with The author, Kirsty Entwhistle. She is one of the Tavistock whistleblowers and was, previously, based at their Leeds branch. You can read Kirsty’s open letter raising her concerns here:

Open letter to GIDS

My son was referred, aged 19, to the Leeds branch of the Tavistock, last year, by my own GP. I have no way of ascertaining who prescribed the cross sex hormones he obtained, just six weeks later.

BFBF1371-4798-4996-834F-E02B42AC5E9C

Yet another clinician raising the issue of detransitioners while the government seems committed to legalising the Woke Gay Conversion Therapy under the guise of banning it. 😳. The abstract references another paper which called for empirical research on desistance and detransition. The new demographic, referred to Gender Clinics, have been documenting their experience in support forums for those who know this was a mistake. It is now urgent that we record the detrans experience, from anecdotal, to clinical research. Thankfully this is now starting to happen.

Here is the abstract to Kirsty’s research.

09A5330C-3292-4F79-8038-C56049E0B8F5

I will see if I can get access to the Butler Hutchinson paper, in full, to add to this series. For those of you with access, to the Journal for Children’s and Adolescent Mental Health, here is the link:

Butler and Hutchinson

As with the other pieces in this series the call is for some formal academic papers to capture the experience of this cohort and commence systematic follow up of outcomes. Gender Clinics seem to have determined that their role does not require formal tracking of *all* their referrals. They need to be compelled to do so they can evidence that this ”treatment” relieves Gender Dysphoria and that medical responses are the only way to alleviate the distress. The decision making process of teenagers and young people also requires more consideration; given how many detranstioners state they did not feel fully informed.

We need a shift in clinical practice to address the root causes of this bodily disassociation rather than funnelling sufferers down a medical pathway.

1207EC2B-80C6-4C72-89AA-60A276B3744C

Those of you on twitter may be aware of Claudia Maclean. This is Claudia’s story as covered by Julie Bindel, in 2007. Claudia continues to speak up for our gay youth, for which I will be eternally grateful. I want a world of true diversity where a gay boy, like my son, with all his variant presentation of masculinity is free to be himself. I do not want a world where he is coaxed into a faux-straight, medicalised closet before he can enjoy a fulfilling, sexual, relationship with the sex to which he is attracted.

AC290535-A392-418B-9D47-975790F37E26

You can read Claudia’s story in the Guardian, of all places:

Claudia’s Story

Modern routes to inculcate Gender Dysphoria in our kids are linked to the rise of the internet and confessional content by transgender influencers. Binge watching this content is something many detransitioners say fostered a desire to transition. In the U.K prominent children’s organisations , such as Childline (run by the NSPCC: National Society For the Protection of Children) promote these transgender influencers in, from my perspective, a reckless fashion. This played a role for my son, in addition to the relentless homophobic bullying that goes on in our schools.

442BE013-330C-4F58-8F57-9169908174B6

Fifteen years after Claudia’s experience no lessons have been learned. The same inadequate assessments are happening to our troubled youth, from within a captured NHS. The role of inducement and coercion is driving our kids and vulnerable adults down a tragic path.

6F18B14E-8D6D-4A95-8317-58D32A699753

NY Times: Product Placement

You are the product. Exhibit A. Who among us does not think this woman seemed in dire need of therapeutic help and not the surgeons knife. Yet here the New York Times are publishing this as a tale of redemption and authenticity. How Mac McClelland went from staging her own violent rape to address sexual trauma to more self-harm. What message does this send to vulnerable young women in flight from the dangers of living as a woman?

This story, coincidentally, came to my attention as I was writing this piece. We learn that the subject is an asexual with a boyfriend. They have already had a double mastectomy and their uterus has been removed. They refer to their ”native penis” sometimes called the ”clitoris”. This is not science It’s a belief system. They talk about how they want to retain their vagina but also it’s a case of ”penis or death” . 👇

3D50EB54-2D88-4546-9F4E-D3A69B4F79A0

The quasi-religious language is common in the phallioplasty files, as covered by the YouTuber Exulansic. The Gender surgeons are the priest class, administering the trans rites required by Gender Jesus, to their willing disciples. It’s a new religion fuelled by the techno-barbarism of the Gender Industrial Complex. Mining profits from our bodies as if there are endless spare parts grown on a human meat farm.

Back to the article:

In a strange way the more extreme proponents of body modification, in the name of the Gender religion, seem to convince the clinicians it’s the right path for their patient. Nobody would do this to themselves unless it was right for them, would they?

Here a detransitioner speaks out, at a meeting I attended. Only when she joined a support forum for women, who had also gone through hysterectomy, did it dawn on her this was a uniquely female experience.

33157763-516E-45FF-82F6-E9DA6A08091C

Some of the people at the detransitioners meeting were themselves involved in the Gender Industrial Complex. If I had sat in a room with young Lesbians who, between them, regretted testosterone, double mastectomies, hysterectomies and ovary removal, I would have left the Industry immediately. Yes, I mean you, Stuart Lorimer: Seen below with Susie Green accompanied by an excerpt from an interview he gave. Our mutilated kids are to fund Stuart’s pension plan.

Excellent question below. Do the NHS and Gender Clinics think about detransitioners when they dish out drugs to our teenagers? Or the Puberty Blockers they are giving to 10 year olds? Personally I would not sleep at night.

E7528DEB-EB34-47D3-8896-83F86C407E1B

Here Bernadette Wren acknowledges the political pressure from third sector organisations (Lobby Groups) on services like GIDS. Mermaids is a pernicious influence on the Gender Industrial Complex. Mermaids CEO, Susie Green, arranged to have her 16 year old son undergo sexual reassignment surgery, in Thailand. Her career seems driven by a desire to justify this decision. Bernadette may also wish to divert attention from the role the Tavistock Gender Identity Service played. She worked there when they introduced the Dutch Protocol and began putting children, as young as 10, on Puberty Blockers.

6BB37082-9254-4656-AB55-51F2C5F52D11

Here is a reminder of what Bernadette told the Parliamentary Inquiry on Transgender Equality. This does not sound like a reluctant, cautious clinician. It sounds like a statement from a social justice warrior . “It is a social revolution that many of us really fought for and wanted around sex and gender”.

2EA9772A-C7F6-4C1C-8735-67816A75C60B

The admission that they were heading in an unknown direction! The breathtaking hypocrisy of blaming the appearance of so many natal females, at the Tavistock, on the failures of feminism! Whilst, simultaneously, facilitating this body hatred with mutilating surgeries!

The paucity of research into psychological underpinnings for the presence of Gender Dysphoria is an international scandal. This is compounded by the failure to follow up those patients who accessed surgical intervention. For me, the moment you advocate for surgery, to resolve a mental health issue, you have failed as a Clinical Psychologist and betrayed your client at their most vulnerable.

87B0D294-709C-46BB-AC1D-3E08C1EE064E

This on breast binding. Its the same old bodily hatred that used to be manifested as anorexia. In this country we have official advice to watch out for girls whose families may encourage breast ironing. At the same time corporate enterprise Lush can offer free breast binders as a marketing campaign!

4C214531-1733-4AB5-A5C7-80CA091F5354

No, Bernadette, you most definitely are not supporting creative expressions of masculinity or femininity. You are telling our gender non-conforming kids they may be born wrong and normalising making yourself a medical patient for life! If you really believe this is what your life’s work was about you are deluded. I would say get some help but where would you go? This is a self-serving justification that reframes the perpetration of extreme harm as necessary and virtuous.

{The Destroy Your Binder video has been removed from YouTube but you can read a transcript on Kat’s Tumbler.}

Destroy Your Binder

Next up Kirsty addresses a response which extols the virtue of a mastectomy for one patient who reports positive feelings about their surgery. This article is not open access but is here:

https://acamh.onlinelibrary.wiley.com/doi/full/10.1111/camh.12343

C7A4F28A-3AE1-4665-8109-FDF12B9F3E78

There are many positive accounts on YouTube celebrating getting your, healthy, breasts removed. To which I say “come back in ten years”. I don’t doubt there may be some who never regret this surgery but there are many detransitioners, as related below, who do and others who find it triggers them on to the next set of surgeries; which suggests it was not the panacea they were sold.

C3DADB2D-3EF0-4D92-BE97-B3BAD5954619

Here Ken Zucker uses the word “iatrogenic” for which 👏👏. The social transition of children and its impact on future medicalisation needs researching. Does it foreclose any reconciliation with birth sex? He also rightly comments on the escalating desire for mastectomy which often follows painful breast-binding. He also reports that bodily rejection migrates to the genitals, post mastectomy.

0727B3EC-A3AB-412E-8142-2786D677C970

The article ends with

9FF736E3-A274-4ABC-BDBA-D19A5389C972

The victims of this modern, mass delusion, are the most vulnerable in our society. Bullied gay youth, girls with eating disorders, autistic kids and kids in local authority care. All groups over-represented at Gender Clinics.

Why has it taken so long to investigate the harms perpetrated primarily on young females in the past decad? The featured image on this post is of a 13 year old girl posing with her surgeon who advertises on TikTok, populated by malleable kids/teens. She calls herself Dr Teetus Deletus to market her services to the youth market.

I do this full-time and have no income. If you want to support my work, and can afford to do so, here is one way.

Researching the impact of Gender Identity Ideology on women & girls as well as the consequences for Lesbians, Gay males and autistic kids. I do this full time and have no income. All my content is open access and donations help keep me going. Only give IF you can afford. Thank you to my generous donors.

£10.00

Detransition Survey: Four

You can read the full paper below. 👇. This is an excellent piece of work and echoes many of the themes found in the earlier studies I looked at for this series.

Detransition Related Needs and Support A Cross Sectional Online Survey

This paper is focussed on the support needs of detransitioners but also covers their motivations to both transition and detransition. It also offers a distinction between those who medically detransition and re-identify with their birth sex and those who end any medical treatment but maintain, or perhaps cling, to a trans-identity.

The first point to make is the paper is published in the Journal of Homosexuality!

B3A1CA36-AFB0-4E4E-8B1D-A9E9F93E4ECC

The location of the publication may, or may not, be a significant development but it gave me significant satisfaction. Below is the abstract for the paper:

904CF38F-5392-4F5C-8DFE-C725CBB925E8

First of all it is crucial to determine the definition of a detransitioner. Not all transition medically so first of all the study defines ”social” and ”medical” transition. It is not always the case that people cease to identify as transgender after they stop medical transition. I am also, personally, aware of a post-operative, de-medicalised male who still uses the term ”transsexual” as he feels it best describes his experience. In this case it serves as shorthand to signal the surgery they underwent and also may be a label maintain community links with fellow travellers.

There is some methodological discussion about how a detransitioner is defined. Some data is based on only those who underwent medical interventions. This paper looks at social as well as medical transition but provides research on which medical steps were undertaken by the survey respondents.

DA7F1EF0-6387-4264-BC4F-67A079EB2B24

For the purposes of this study the author has chosen to focus on those who claimed the label ”detransitioner”. However, they did include 8 people who rejected the label but whose experience was deemed to be sufficiently analogous to include as a ”detransitioner”.

It is also important to note that there are some trans-identified people who feel they have followed an irreversible path. They believe to re-identify with their birth sex is simply not socially, or medically, achievable. I know both males and females, who find themselves in this sort of limbo or no wo/man’s land, if you will. The author is aware of this complexity but it is outside of the scope of this study.

C1C9E046-161D-4402-A08B-C1F7F113ABEF

Survey participants were identified by targetting people in on-line forums, where detransitioners were known to seek suport. They were asked a simple question about whether they had ever socially/medically transitioned and stopped. Details of the survey sample are below 👇. As you can see females are over-represented. I suspect this not only a function of the new demographic being predominantly female. It may also be indicative of female openness to seeking community. Perhaps, it also suggests males are less likely to, publicly, admit they made a mistake. Note that males also seem to take longer to find their way back, to their sex, so this pattern may change in the future.

The survey had global reach with majority representation from the United States followed by Europe.

CF40C9EC-D469-42B9-A742-E4DA12775D74

The majority transitioned socially and medically. As this comment reveals there is further complexity in that someone asked about a category for ”Med-trans” only. I assume this is people who didn’t disown their birth sex but did have medical interventions. This may be a niche issue but note that the current WPATH (World Professional Association for Transgender Health ) guidelines have a section on Eunuchs. No I am not kidding!

C0D681F4-3E7C-4533-A12D-4B10BF48B005

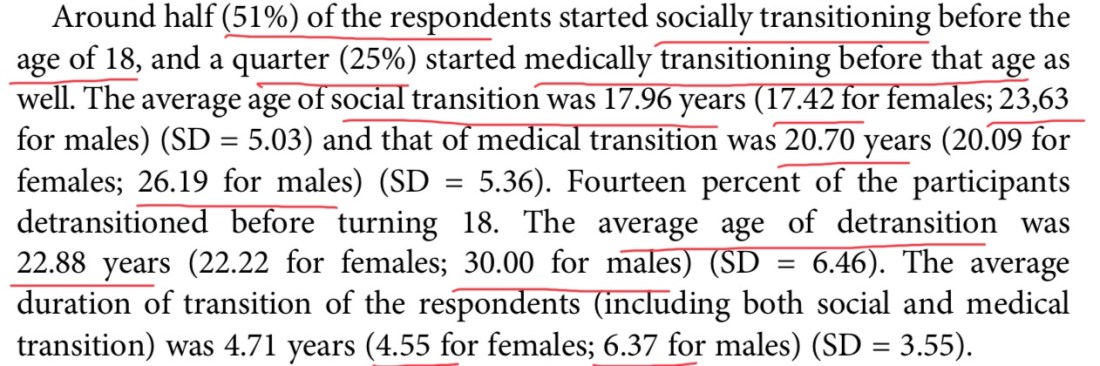
Below the author delineates the reported experiences revealed by the survey: 51% started socially transitioning under the age of 18. Average age of Medical transition was 20 for females and 26 for males. Brain maturation estimated to occur around age 25. Detransitioners emerging from cohorts who did this at the age of legal majority, the majority, are in danger of being left unprotected in any future which restricts irreversible treatments, in under 18’s.

FDC8884E-1CC6-4053-AFC5-EF0DE969AF9F

The sample of males was not large but the age of onset of medical transition mirrors what I have seen on other de-trans surveys. Girls tend to start earlier and spend less time transitioning. Not for the first time, I am struck by how sex matters even in communities which furiously deny the significance of biological sex.

Next up the profile of the respondents. The high % of co-morbidities is also a familiar finding. The rates of surgical interventions is also staggeringly high (46%), especially given the length of time the respondents, particularly, the females, identifed as ”trans”.

The table showing co-morbid conditions lays it out rather starkly. I would have preferred to see sex recorded against these conditions but as the number of males was small it may not have revealed any, statistically, significant differences. Sorry, not sorry, I am wedded to the sex binary. 😉

03953D1E-3916-4C4C-9078-DE2859551309

Now we come to look at reasons for detransition, that are also, inevitably, reveal the reasons for transition. I notice that, in marked contrast to studies funded by Trans Lobby groups, lack of social acceptance/ discrimination scores quite low. A staggering 70% realised their Gender Dysphoria was rooted in other issues.

The kind of support needs the detransitioners identify reflects further on reasons for their initial decision to transition. Many 👇were wrestling with internalised homophobia. See also the comment about a shift in Gender Identity. It is logically incoherent for Trans Activists to argue for the recognition of “Gender Fluidity” whilst defending irreversible interventions for children and adolescents. I am also pleased to see the discovery of radical feminism makes an appearance. It has also appeared in earlier surveys of detransitioners.

2DDB07C2-A67F-459E-BBB0-E3FDEE2ACF5B

The survey also allowed for open comments which I have reproduced in full in part (4 a) to this blog. Well worth giving voice to all the detransitioners who opened up about their experience: You can read their comments here 👇.

Open Comments Detrans Survey 4

The open comments reveal the ostracism, from the LGBT community, experienced by those desisting from the trans-narrative. They also speak of the betrayal and mistrust they now feel towards Medical professionals. The difficulties of finding therapists able to deal with detransition also features in the open comments.

The survey

55A20BE1-4817-4BF0-B607-3FD2893DA727

The survey also provides a helpful table which compares and contrasts the sources of support respondents enjoyed while transitioning and detransitioning. As you can see the LGBT community and trans specific organisations largely leave the scene of the crime; once people realise they made a mistake.

F1B4D943-98B1-424E-9D6C-421C38DC7C30

The survey continues to identify the kind of support the respondents would like to be available. These cover psychological, medical, legal and social categories. Counselling to deal with issues such as internalised homophobia, sexism and feelings of regret. Medical support to deal with stopping/changing cross sex hormones or complications from surgeries. Social support covered the need to hear other stories of their fellow travellers and the need to meet up, on-line and in real life.

3A21350B-2FD7-42E2-98CA-EB913F7E6365

The legal support mainly related to the need to re-establish their legal identity as their correct sex but a small percentage wished to take legal action for the injuries caused by the medical interventions. 👇 Those of us waiting for legal action, to put an end to this cannot, in my view, expect detransitioners to shoulder this burden. But, if those 13% do take up the legal fight there will be an army provided to support and fundraise for them.

Politicians need to do their jobs and start legislating. They also, in the United States, need to close loopholes relating to Statute limitation. Many live in states where the average length time before detransition means they are already out of time to get any legal redress.

519A884B-3654-496B-92CA-6CF6200BA4DD

I do this full-time and unwaged. If you can afford to support my work you can do so here.

Researching the impact of Gender Identity Ideology on women & girls as well as the consequences for Lesbians, Gay males and autistic kids. I do this full time and have no income. All my content is open access and donations help keep me going. Only give IF you can afford. Thank you to my generous donors.

£10.00

DeTransition: 4th Wave Now (3)

This post is based on work done by a detranistioner. It was linked to the paper I covered in this post:

Detransition: Cambridge Study (2)

As stated in my earlier pieces getting access to detransitioners requires seeking them out on the social media apps they use. The research was published on Tumblr:

https://guideonragingstars.tumblr.com/post/149877706175/female-detransition-and-reidentification-survey

The work provoked a furious reaction from within the Trans Industrial complex, which you can read about here:

https://4thwavenow.com/2016/09/03/top-gender-doc-dismisses-203-detransitioned-women-as-not-regretters-per-se/

Dan Karasdic likens the work to previous research done by Evangelical Christians and then follows up with a claim the detransitioners were “never really trans” 

041283B7-F73D-4BB6-82CD-175E680107A1

Judge for yourself.

Methodology:

Cari, the author reached out to people who had desisted from a trans-identity with a survey opened for only two weeks, in 2016, which attracted over 200 responses.

A217741C-13CE-409D-BD94-0F8471250417

The resulting data garnered some real insight into motivations for a medical transition and subsequent detransition. The survey allowed for the inclusion of people who had ended a medical transition but remained ”trans-identified”. The vast majority identified as female with quite a few rejecting the prefix ”identified” ,as female, to state they simply ”are female”.

10FBC7C8-9378-40C5-BF00-59FA08884F90

This is what the graphic representation illustrates:

EB481811-F6AE-4BED-BE78-8567C2FE835F

For those who did not claim a female identity the breakdown was as follows together with a graph of how they had identified while transitioning. As you can see the majority identified as “trans men” closely followed by “non-binary/gender queer”

A94773B5-3553-4570-B688-1E704CD031AE

The survey also tracked the ages of both embarking on a “transition” and detransitioning: The average age for coming out/starting transition was 17 years old and beginning detransition was aged 21.

9D7BEE9B-BCED-41DC-AEE7-E6423A39D639

The research also looks at what kind of dysphoria the women experienced. The majority reported they had both social and physical (Sex) dysphoria. That is they desired to have, facsimile, male sex characteristics and a desire to be treated as male or, at least, as other than female. This group constituted 74% of the surveyed.

A82D7C4C-6311-4FF1-93F9-DC9CFAB58497

The report goes on to detail that 88% experienced ”sex dysphoria” ; something often denied by those who do not want the topic to be discussed. A claim also rejected by those who argue that detransitioners were never really ”trans” and didn’t have dysphoric feelings.

3CE37541-0542-4BF1-8C03-BE967FC28D39

The research also questioned the particpants about their experience of detransitioning and its impact on their well-being.

ABB4D2F8-E452-4491-91C8-67669B30E5E4

The majority found an improvement in their dysphoric feelings after detransition, some reported these feelings had completely gone. There was also a small minority finding their dysphoria had worsened since they began detransitioning.

The survey uncovered some serious concerns about a lack of counselling with a mean duration of less than three months, even for those who did get therapeutic assistance.

9B331360-A63C-4D22-93E4-0537BC9AB4FF

Of those undergoing a medical transition the figures for those who had zero counselling was a whopping 65%. These women had no therapy whatsoever before embarking on medical transitions.

B9FD6A3D-AE4A-433F-9724-421F4783A13E

Next up the participants were asked what led them to detransition. The top answer was due to political/ideological concerns. The next popular answer was finding an alternative coping strategy. 30% had concerns about their mental health and over one in five reported medical concerns.

4B1A8ED5-1A0D-4F86-AA57-FE6B5524B0D6

The survey provided space for open comments which allowed participants to expand on the reasons for their answers. They were asked to state their position /feelings about their own transition and on the idea of transitioning more generally. The study found participants were generally more negative about their own experience than they were about the idea of transitioning, more generally.

60% were more or less negative about their own experience with a slightly lower percentage more or less negative about transition for other people.

4D50E319-17D9-42DF-9F96-CCC0A57915AA

The open comments were revealing. Discovery of radical feminism is mentioned, as a positive, by a few of the participants. Support from Lesbian communities, or lack of such a community is referenced. Some felt they had been pushed into transition. Lack of alternatives presented by therapists also cropped up. Here are some comments on their own transition: Here reports of pressure, feeling duped, crops up. Also one woman feels she has so altered her body with hormones, mastectomy and hysterectomy she feels as if she is no longer allowed to identify as a woman, or a man.

7EBB5A1D-C281-408F-9A45-C2DE1F4F4295

More comments about the lack of exploratory therapy, inaccurate information from trans-activists, no effort made to consider non-medical responses to Gender Dysphoria recurred. The therapeutic community has a lot to answer for, in respect of this unfolding medical scandal.

BEE855D2-FF74-4D62-B1DD-0924D1DA62A7

More comments reference the need for a stronger community for Lesbian and bisexual women. Even among the detransitioners there is still a belief in Gender Identity Ideology /Queer Theory and one also remains in a relarionship with a ”Trans man” who remains on a medical pathway. Only some are critical of medical pathways more generally, but the majority express the need for careful consideration and more therapy.

AAC6A05A-3B70-4E06-B161-7C2095095B37

One respondent succintly states :”Burn every gender clinic down”. Many also express concern about children and teenagers put on a medicalised pathway. Lack of attention to trauma, underlying a flight from being female, is also a recurrent theme, as is the lack of accurate information from the trans community and medical professionals.

More than one respondent likens the transitioning of children and young people as a from of conversion therapy. The expressions of anger at those who colluded with this are surprisingly muted. Many seem to blame themselves but one, rather poignantly, wishes people, had been honest rather than encouraging her down this path. A few respondents do, however, blame queer theory or the trans-medical system. In general they show compassion for those who continue on this path or are about to embark on medical intervention.

I firmly believe the poster who calls this “medical recklessness” will be vindicated. Dan may rue the day he dismissed these findings. 👇

288D7DA3-2FE3-4E67-BA96-4D0A04F3CB14

I do this work full-time and unwaged. If you can afford to support my work you can do so here: 👇

Researching the impact of Gender Identity Ideology on women & girls as well as the consequences for Lesbians, Gay males and autistic kids. I do this full time and have no income. All my content is open access and donations help keep me going. Only give IF you can afford. Thank you to my generous donors.

£10.00

Detransition: Cambridge Study (2)

Finally there seems to be some recognition of the phenomenon of people who detransition. I come to different conclusions than the authors and I have some questions, but this study is worth looking at. You can read the full paper here:

Access to care and frequency of detransition among a cohort discharged by a UK national adult gender identity clinic- retrospective case-note review | BJPsych Open | Cambridge Cor

The researchers looked at rates of detransition in patients treated at a UK Gender Clinic.

47DABDDE-2AA2-44E2-B15E-6F06A3EA00B5

Pay attention to this. We are about to introduce a more ”streamlined” service for Gender Identity Clinics (GICs) but we do not know how many people detransition! What struck me, repeatedly, was how much this report laments the lack of data in this field.

This was the methodology. They looked at all patients discharged in a period of a year. They then looked at a number of variables to see if there were any common factors in those who they determined were ”detransitioners”. This is important because they aimed for a consensus view about who met the criteria to be counted as a detransitioner. The danger with this approach is that it could be distorted if any of the people doing the screening was driven by a belief in “Gender Identity Ideology”.

297EB842-D17E-4A87-A14A-3BA5B6548684

As you can see they use a definition which is about “living in a gender role”. I flag this because a Butch Lesbian may discontinue medical intervention but may still be deemed to be living in a ”masculine” role. She may not see it this way, she may see herself as a woman who is not confined by sex stereotypes. Similarly a gay male may detransition and still have atypical interests for his sex. Are these two, potentially, discounted because of their ”Gender role” ?. Other people may feel that they have reached a point where there is no going back because of the irreversible nature of the interventions. They may regret the changes but they won’t count as a detransitioner.

C7C27DE1-A6C0-4E83-99ED-C75B4DAA8449

Leaving aside this question we turn now to how many of these, discharged, patients were originally flagged as potential detransitioners. The figure they agreed on was 12 people who, it was agreed by consensus, met the criteria:

2ED68105-4F20-485A-9754-51ADF3DD3052

The numbers were whittled down to 12 from an original sample of 21. If the criteria they used is erroneous and those 21 would meet a broader definition of ”detransition” the figure would be 12%. This does not include the three suicides. Even excluding the suicides the percentage is nearly double the % calculated by the studies authors. In one scenario a person may not wish to abandon their identity as a ”Transman” which may be the source of their community. Given the negative responses to those openly expressing regret and coming out as a ”detransitioner”, from the LGBTQ+ community, some may remain in the closet. All of which is to emphasise the point that the definition of regret /detransition is significant in determining who counts and, crucially, who doesn’t.

23BFFFB5-C534-4F13-9191-C0EEEE59C9DF

Other detransition studies:

The paper highlights that other studies have set the rate of detransition from anywhere between 1% and 8%. They reference the source for both those figures. The 8% figure is from a United States, Trans Equality Survey, from 2015. That survey was funded, in part by the Arcus Foundation.

8089C49F-B135-4280-AAED-5AD166A257F5

Arcus Foundation are huge funders of organisations disseminating Gender Identity Ideology as are the other foundations listed, above, as supporters. I wrote about Arcus Foundation here:

ARCUS FOUNDATION GRANTS

The survey explained the phenomenon of detransition thus:

F4C321B0-8798-4A86-A208-58A4F2C9C976

The common rationale for the phenomenon of post transition regret, or detransition, is to locate the reasons in a lack of social acceptance. An alternative framing is the realisation that it is impossible to change sex it is possible that living with the psychological, and medical, consequences may create an intolerable burden.

The other study referenced, by the authors, is this one from 2019. The methodology was to access a random sample of patient notes to examine whether the patients expressed any regret. The authors are keen to point out detransition can be seen as part of an exploration of their identity. This is a frequent rationale and sometimes described as part of a ”Gender Journey”. This sits oddly with the push to irreversible medicalisation and injunctions to listen to the patient when they demand access to treatment. Note the conclusion, if so few detransition there should be no reason to slow down the treatment pathway. 👇. Richards, the co-author, works at a Gender Clinic.

Another source (not quoted) also found only 1% detransitioned. The methodology appears similar. A years worth of clinical notes were scanned for words indicating regret or detransition. This study has similar limitations to the one I am looking at here. It’s only a snapshot, the authors define what they regard as ”detransition” and there is also a lack of recognition that dissatisfied patients would, potentially, be unlikely to notify the Gender Clinic.

Their findings are listed below:

FEA7D0C2-1659-4210-B042-3D10ECEF840F

Back to the Cambridge Study.

Here is a table giving an overview of the kind of co-morbidities the patient group are also wrestling with 👇. As you can see there are high rates of mental health issues; over 80% in the under 25, male group. Looking at the pattern for accessing mental health services many of these co-morbidities appear to be going untreated. Rates of self-harm are notable in the female, under 25’s. Nearly 90% of the younger females also had at least one adverse childhood experience.

A7425775-FF08-42E4-B6B5-B445DBF80BC8

In the table above it is the females over 25 who have the highest percentage of suicide attempts. Buried in the report is a reference to three, completed, suicides. There is no further information about the sex of the people who committed suicide and no intelligence as to whether this was attributed to the medical treatment they accessed. If these were linked to post-transition regret that would be another three to consider.

B898212E-7103-44D5-A98B-6F46E797503E

Below, more information is supplied about those who met the threshold to be defined as detransitioners. One, a male, had completed Genital Reassignement Surgery, which, I presume means removal of the testicles/penis. Again, I would imagine re-identifying as your natal sex would be especially challenging in this circumstance. All the females had accessed double mastectomies.

A7F33E78-D5C4-4C75-BEBE-E59BE33FA156

The authors of the study do recognise the limitations of their research, as well as the dearth of studies in the field. They do recognise that there is much loss to follow up and no consistent way of tracking those who detransition. They also recognise that GICs are dealing with a 40% increase in referrals and they are treating a new, adolescent female, demographic via service specifically designed to meet the needs of older, males. However, like the earlier studies they are reluctant to let go of a more streamlined service, for which read lower levels of gatekeeping and faster progress through the system.

CC1EC01D-E460-461E-99FC-0CFA8856DE2F

The authors also question the use of notions of regret in this community; using the kind of language associated with those who talk of ”Gender Journeys”. Such language masks the fact that there is no way to reverse surgeries like double mastectomy or GRS, or even Testosterone usage. This sophistry seems designed to obscure rather than illuminate.

072E85BF-3BBD-424B-ADA4-DC01F6F2B8E9

Note also 👆that they recommend including “trans” people in research and service development but not detransitioners.
So, in summary, more research is needed, loss to follow-up remains a problem, GICs need to be compelled to evaluate all those who have accessed medical interventions. The definition of detransition remains contested. For those who choose not to return to the GICs there has to be a mechanism to track their outcomes. Sadly, there is also now a need for a service for detransitioners; some of whom may need to rely on synthetic hormones, for life, having no means to produce these naturally.

Another important acknowledgement of the studies limitations points out that research shows regret can take years following treatment. Even the authors acknowledge they may have underestimated rates of regret/detransition.

A4714E02-697B-410C-86EB-A3E1650EF8EB

You can read part one of this series here:

Littman and Detransition

I do this work full-time and am unwaged. If you can support my work it helps me keep going.

Researching the impact of Gender Identity Ideology on women & girls as well as the consequences for Lesbians, Gay males and autistic kids. I do this full time and have no income. All my content is open access and donations help keep me going. Only give IF you can afford. Thank you to my generous donors.

£10.00

Manufacturing Moral Panic 2

Why is a network of Charitable funding bodies fuelling a backlash against women’s sex based rights? Why are organisations, set up to protect children’s rights, teaming up with organisations promoting Gender Identity Ideology?

For part one see below 👇. My previous post showed the links between these foundations and links to some of my earlier work examining the activities of *some* of these organisations. It also contains the link to the, 131 page, document endorsed by Global Philanthropy Project and Elevate Children’s Funders Group.

Manufacturing Moral Panic

In this post I want to cover the opening letter explaining why this coalition was established. I will also highlight some of the terminology they use in the glossary of terms. This is how they characterise women defending our sex-based rights. We are ”Gender Restrictive”. Heaven forfend we are simply called feminists because then it would be abundantly clear they attacking Women’s rights!

1733696C-EE69-48C3-A0AC-348D9F2B0619

The coalition makes sense in one respect. Much of the opposition, to the spread of Gender Identity Ideology, raises concerns about the medical interventions perpetrated on children. By which I mean blocking puberty and introducing cross-sex hormones, all to cement a Transgender Identity; this despite the same ideologues arguing that “Gender can be fluid”. I have covered Puberty Blockers many times on this blog. For neophytes, or as a reminder; in the U.K we are giving Puberty Blockers to children as young as ten, on the NHS. They, almost, invariably progress to Cross Sex Hormones and as a result they will be sterile. It therefore a significant concern that a coalition of children’s charities have signed up to this document.

The authors recognise that childhood is defined as up to the age of 18 by the Children’s Rights Coalition (CRC). It nevertheless claims ”adulthood” is influenced by the social context in which the ”child” lives. As far as I am aware we don’t defend child marriage, or child labour, even where a child is based in a country, or culture, which normalises these practices. This blurring of the boundary between child/adult is necessary when arguing children have the right to bodily autonomy in respect of accessing “Gender Affirming” care. I believe this is why Children are being reframed across a myriad of public /campaigning bodies as mini-adults.

A0333A69-2C1D-4FEA-AC2C-0B26CA63894C

I am glad they reference brain maturity because credible research states that brain maturation continues up to the age of 25. One of the key battle grounds, for the promotion of Gender Identity Ideology, is to argue for the empowerment of children. This allows arguments, for children, especially teenagers, to access medical interventions to cement a trans-identity, without requiring parental consent.

Brain Maturation

Here’s the abstract for that research.

C0CC1BD0-3942-4E46-B09D-9AA9C01D9229

Just a reminder about UK Law on getting a tattoo. It is not legal even with parental consent.

7C428299-122D-4A5F-8DF0-4FDBDEC2DE12

Next up the document quotes the Committee for the Rights of the Child (CRC) again. Note that the document explicitly references sex but the author’s quote another document to claim that this also covers ”Gender Identity”. Once again, this is a common tactic a sleight of hand to claim the law is in your side, even when you are arguing for it to be changed. A good example is the public campaign to allow anyone to ”Self-Identify” as the opposite sex and the more covert campaign to abolish single sex spaces. When it appears these laws are not going to change (outside of Scotland) campaigners are simply lying about the law to get it built into policy. [Hence the twitter hashtag #StonewallLaw].

665B20CC-0A0A-457D-8351-64E63AC762B2

Note the small print on this which references the ”transsexual” child. 👇.

402529D9-0FD8-4965-8475-74EA37188FBD

Heres another interesting aside. The rights of the child must take into account the child’s views. They also posit the view that the argument of “Best Interests” cannot be used to justify actions “inconsistent with child rights”. In the context of Gender Identity Ideology this is often deployed to argue children/adolescents have the right to bodily autonomy and to access ”Gender affirming” medical interventions. This takes us back to the notion of “transsexual children”; a description usually avoided.

3584886A-C431-4B4D-88F9-DBFED0AA8AAF

Glossary of Terms

The glossary of terms at the beginning of the document are illustrative of the ideology under-pinning this document. It includes the newspeak of Cisgender, Transgender, Heteronormative, Assigned Sex at Birth etc. Intersex also makes an appearance despite this not being favoured terminology among those with Disorders of Sexual Development (DSDs). The term ”intersex” won’t be given up without a fight because the Transgender movement use people with DSDs to muddy the waters and suggest there are more than two sexes. (Humans are, in fact, Sexually Dimorphic).

I won’t treat you to the entire glossary but its worth including a couple of examples. Under Gender and Sexual Diversity can be found the definition of sex. This recognises biological sex only to claim it is randomly ”assigned” . They also claim sexual dimorphism is based on a common belief in a binary sex classifications. This equates scientific accuracy to a faith based position. In this section 👇 the author’s also feign allegiance with the interests of people with DSDs; who often campaign against unnecessary surgery on infants. Note that some surgeries are in fact medically necessary, DSD activists oppose only cosmetic interventions on those under age.

The section dealing with SEXual orientation is below. Of course they define it as a Genderal Orientation. And we must have a category for the oppressed asexuals or as I call them ”the shag anything that moves brigade”.

7AE43F75-71D9-4B24-B665-67AD9CCA77C8

Whoever named Pansexual after a mythical, horny old goat at least had a sense of humour: 😂

403ABD27-FF76-451F-9EE3-F8163AFD35A2

So far, so predictable. Now we get to the definition of ”Gender Justice”. Note that the definition includes (cis) women’s rights. Yay, we actually get a category of our own! Don’t get too excited, it is prefixed with the insulting ”cis” and, read on sisters, they graciously deign to consider redressing the power imbalance between men and women “if necessary”! I think it is FUCKING necessary since you are re-defining us against our will.

01D52390-F589-464D-9015-BCDDC5F743B6

Introductory Letter

Now we get to the letter accompanying the document which purports to explain why they felt it necessary to join forces to expose ”Gender-Restrictive” folks. This is newspeak for Witches, by the way. 👇

F9BEB02B-2473-43D0-AC5D-8FF5968E33E0

It is hard to credit the claims made in this document and the level of testeria fuelling the authors of this ”research”. For those of you familiar with DARVO (Deny, attack, reverse victim and offender) this is a classic of the genre. Apparently WE are distorting huMAN rights. Which is a bit rich coming from the Gender Ideology lobby who are all about the MAN in human.

We are also being accused of ”anti-democracy”. I cannot think of anything more anti-democratic than following a blue-print that encourages the passing of laws, by stealth and avoiding press-coverage. (See the Denton’s document. Blog below). More D.A.R.V.O.

That Denton’s Document

Gender Critical Women as an “Alarming Trend”

4F363240-E68C-4A94-94F4-00C330CB67BF

Women defending sex based rights, Lesbians refusing to accept males as sexual partners, mothers fighting to stop the medicalising of, among others, gay and autistic kids, are planning State Seizure! They actually sound crazy! Below they even claim women, fighting for sex based rights, are actually the ones attacking women’s rights.

4ECF161F-4D54-4584-842C-3CF03A1CE4F7

Yes, there is a threat to children’s rights as activists are inculcating “Gender Dysphoria” in our kids and teens. Schools are teaching children a lack of adherence to sex stereotypes equals #BornInTheWrongBody. We are coaxing our gay youth into faux-straight, medicalised closets.

They also fear this Moral panic is effective. If it is effective this is because it is rooted in truth and (biological) reality. For the avoidance of doubt they do mean us! Here is a reference to ”So called ”gender critical” feminists. Nobody is arguing against human rights for trans identified people, in GC circles, we are fighting for sex based rights for women. No Conflict They Said. So, why does every fight for women’s rights garner an “anti-trans” label.

  • E6C465B5-ED72-4738-B95B-9E89F8C08EC2

Seriously they think we are well funded and have been planning this for 35 YEARS! I wonder why they didnt choose Terf Island (United Kingdom) for their country analysis? Could it be because it really doesn’t help their case? What with so many of us being Left-Wing, Trade Unionists.

48FACF4C-06A5-4A73-9E26-5E84475DF18C

The authors sound a warning to its disciples that they must unite to oppose the evil terfs and band together. Right side of history and all that.

DA5B6EAD-4D62-444E-8503-36F5306912A5

I will leave this post with a list of the organisations that contributed to the document which includes Comic Relief whose funding is regularly used to promote bodily rejection.

6D860974-49E8-4751-BC79-C7BF4670AB8E

I am going to do more on this document especially on the scurrilous attack on Womens Human Rights Coalition (W.H.R.C). I also have sisters from Bulgaria, Ghana and Peru looking at the country specific sections.

Finally those of you who are clearly sitting on the mounds of cash spare a bit for a sister! I seem to have missed out on the Swiss Bank account enrichment. 😂

Researching the impact of Gender Identity Ideology on women & girls as well as the consequences for Lesbians, Gay males and autistic kids. I do this full time and have no income. All my content is open access and donations help keep me going. Only give IF you can afford. Thank you to my generous donors.

£10.00

THE APARTHEID OF SEX: Rothblatt

Who exactly is writing policy for the Ministry of Justice?

This blog is going to focus on what Rothblatt had to say about prisons. Rothblatt has a lot to say about a range of issues; as a late-transitioning transsexual with an interest in Trans Humanism. I will do a series looking at Rothblatt’s ideas across a range of topics impacting women. Women are a SEX CLASS not an “identity” for men to claim whether it is done as an act of dominance or as a refuge. We can support males who reject their masculinity but no ally would claim to be the same as a woman; especially now the damage, to women, from Gender Identity Ideology, has become apparent.

Martine lays out his vision in his manifesto for a new “sexual revolution”. I find that an interesting choice of title because, from my vantage point, this is the perfect description. This a Men’s Sexual Rights movement masquerading as the civil rights issue of our time.

A261B8D5-E068-4276-A6F6-CB58DF8E93C4

In this book he argues that the categories of male and female lead to a sort of apartheid, which is how he categorises sex segregated spaces. Martine argues his proposals have emerged from feminist thinking. When a man like Rothblatt starts, approvingly, quoting feminism, he is either going distort it beyond recognition, or he is quoting Dick pandering, doormat, ”Feminism”

I did a long thread, over on twitter, about Martine Rothblatt which you can find here:

@STILLTish Apartheid of Sex

A modest proposal for the Prison System.

What does this Martine’s vision have in store for women in prison? Martine argues that the justifications for sex segregated prisons are postulated on the basis of women’s “frailty”. He argues that these claims are suspect.

B6FBD5DF-E896-44C9-B526-23FB2AE1167F

Before I continue here are some facts about the U.K Prison estate. 👇These were published in 2020 and represent the data as of November 2019. Please be aware that, stark as the sex differences are, some of these offenders are males allowed to blame their crimes on women. Despite this, state-sanctioned, gaslighting, the male-inclusive, category of women is still a tiny proportion of the prison population. Women are less likely to be imprisoned for crimes against the person and only 2% are recorded as imprisoned for sex offending. Note that some of those “female” crimes are actually committed by males. Thanks to a recent court case we now know that there is an over-representation of male “women” incarcerated for sex offences. With such small numbers even one male added to this category of criminal offences can make a huge difference. Hence we have an entire programme on the BBC expressing horror at an 84% rise in female paedophiles. Are they female? Really? Shamefully the BBC chose not to question the data, Fairplay For Women did, see link below.

Female paedophiles rise by 84%?

He goes on to argue for his own solution to prison accommodation in a novel version of carceral feminism. Unbelievably he argues sex segregated, prisons have done nothing to stop rape in prisons. What he fails to mention is he is talking about male on male rape! (See below). Of course the Prison Industrial Complex, especially after the introduction of the profit motive, keeps costs low by providing low staff to prisoner ratios. I don’t disagree that the prison system fails to protect vulnerable, male, prisoners in the male estate. Prison reform campaigners have long argued single occupancy cells would reduce the numbers of men raped and murdered. Yet the solution selected has been to place, actual, and so called, “vulnerable” males, claiming a female identity, in the women’s estate. This has resulted in male sex offenders being housed with women, illustrating the naivete, or worse, nefariousness, of the architects of the policy. A system which denies women’s need for sex segregation and prioritises the needs of males, is a blatant example of institutional sexism.

1526B04F-FD9C-48C3-87ED-62485F1B42CB

Even worse is that final sentence. Men are to be allowed to mix with women because it may help with their rehabilitation. This is woman, as support human, territory.

FARMER V BRENNAN

Here Martine quotes a court case from 1994 where a be-penised inmate, who Rothblatt calls “her”, sued the government to be moved out of the prison where he was held. Ruth Bader Ginsberg was also involved in that case, but didn’t act for the prisoner.

CBD0ED8E-C3FD-4B24-82DD-08861E2AA17C

I took a little detour to look at the Farmer case. Dee Farmer had a twenty year sentence for credit card fraud. They appear to have been moved to a higher security prison following further offences in the prison estate. They were a pre-operative “transsexual” in terms of being penis-intact. They had been transferred to the higher security prison because of a continued pattern of criminal offences. (No violent ones were reported or sex offences against women).

62C67A74-443C-4AE7-814C-0EFC2307D1F2

Dee was moved to administrative (segregated) detention due to engaging in consensual sex, whilst HIV positive. Farmer was seeking a move to a lower security prison with less violent offenders. Ruth Bader-Ginsburg drew attention to other groups of vulnerable male offenders in the oral arguments. In my darkest (or more realistic?) moments I think the madness may end when other (Gay?) males claim discrimination because they are being treated less favourably. Maybe men will be listened to and effect some change? Policy makers and politicians are clearly comfortable with ignoring the negative impact on women.

They were not asking to be moved to the female estate having dropped an earlier petition as detailed below. Undoubtedly, were this case to be brought today, the claimant would have targetted a move to the female estate.

4D05614D-D910-4620-8156-1193DCC5F6A9

BACK TO ROTHBLATT.

Now we come to some of the practicalities of this new utopia. Here Martine has to deal with the fact that women exist, as a sex class, and the fact it is the female people who get pregnant. How does he propose to get around this? We will forcibly implant contraceptives in the women and suppress sperm production in the men. The risk of pregnancy, he argues, can be remedied by a pharmaceutical solution which he is quite happy to be “mandatory”.

82E97D85-B6D9-47E4-A057-C1E4FA77F689

Here he avoids the use of woman but reduces the inmates to their “genitalia”. The use of “accidental pregnancy” also avoids having to confront whether these pregnancies would be the result of rapes; a distinct possibility when female prisoners are confined with men. Nowhere does he address the fact that 99% of prison convictions for sexual offences are committed by the male sex or the fact the female population will be vastly outnumbered by the men.

6EBAA27B-2A03-4D94-B342-A24300975F07

In summary, Martine constructs an argument which ignores the significance of biological sex in determining likely predators and prey. He leverages the clear vulnerabilities of a pre-op transsexuals. He conveniently ignores likely vulnerability of other young males; who may be gay and also deviate from accepted performances of masculinity. Worst of all he is prepared to expose women to serious risk because he cannot bear any division between his imaginary female identity and actual women. This is the misogyny peculiar to autogynephiles.

He then proposes the barbaric, and likely illegal, mandatory contraception for women. He shows little concern this is necessitated by the higher risk of rape. As an aside he claims that mixing the sexes may encourage lower rates of recidivism, a spurious claim given that you are providing sex offenders with captive prey. These men are not known for their restraint.

This book is from 1994. Had I encountered it at the time I would have dismissed this as merely the work of a deranged mind. Never could I have imagined it as a blueprint for the future. In 2021 it is eerily reminiscient of official Ministry of Justice policy and that should enrage us all.

You can support my work here. Only do so if you have surplus cash I know many people are struggling.

Researching Gender Identity Ideology and the impact on women; the female sex class.

£10.00

Looked After Children & Gender Dysphoria. 2

Wallace Wong 

Wallace Wong is a Gender Identity Specialist based in Vancouver. He boasts that, of the 1000 children in his care, 500 are children from the looked after system. That is children who are, in some way, wards of the state. Wallace Wong works for the Ministry of Children and Families and also has a private practice.

8A0F31F7-F5D8-4974-A974-45088D1473CD

He arrived at his current career path after noticing how many “transwomen” were impacted by the HIV/AIDs crisis. He initially began working with adults but soon noticed that the age of those with “Gender Identity” confusion was becoming increasingly younger.

196D72AB-3656-4B63-8AB8-262631EC3E56

You can listen to the full audio at this site. I imagine that many of you may diverge from their larger aims (as do I) however, given the dearth of coverage in other media outlets I will link to their research. This is the only way to honour my commitment to provide primary sources, where possible. The link is below.

Wallace Wong

The clips in my piece were included in the vimeo embedded in the above link. I have listened to it, in its entirety, and can attest to the accuracy of the transcribing. It is a long presentation and I can’t do justice to all of the issues it raises but below is a brief overview.

Wong argues that we must not confuse gender incongruence/roles with being Transgender but most of the examples supplied are of boys who like “girly” things. Expect lots of references to princesses and pretty things. He dismisses research showing high rates of desistance in children who, historically, claimed a trans-identity. He argues that “gender” is innate and quotes some research about hard-wired neurological causes based on MRI scans proving #LadyBrain. He also quotes some self-reported adherence to sex stereotypical behaviour, typically associated with the opposite sex. I suspect Wallace has not heard of the, Shakespearean, quote “the wish was father to the thought” (Henry IV, Part II). We are treathing retrospective wish fulfilment as if it is peer reviewed evidence. Laverne Cox & Caitlin Jenner are wheeled out to confirm the idea that children know they are trans age three. Caitlin, you may remember managed to father five children and win Olympic medals during his male life. Laughably, at one point a video commentator appears to think the existence of Facebook “genders” has some sort of evidential significance.

He is also at pains to dismiss any concern that confusion could arise between emerging homosexuality and a proto transkid. Similarly he argues that high rates of autism can be expected because both autistic traits and transgender traits are biologically determined. High rates of co-morbid mental health issues are to be expected, he argues, because being transgender is hard.

EAF47212-6FA9-472E-86BF-7833D83D2D9D

Below Dr Wallace seems keen that we should know he is seeing patients as young as 3. He also makes it clear about the fast pace of this change and the fact that research has not kept pace with this development.

56612443-A99D-4A93-9A99-17C877E40AD4

Below is where Wong makes the startling admission that 50% (500 out of his 1000 referrals) are from the Ministry of Children and families. This means they are somewhere in the care system and commonly referred to as “Looked After Children”. Dr Wallace doesn’t appear to have much professional curiosity about the exponential growth in “transkids” over this period.

Jenn Smith (also based in Vancouver) is a male who expresses “feminine” and ascribes this to his experience within the care system. Jenn argues that children in care are particularly vulnerable to “identity” issues which also extend to “gender identity”. It was Jenn Smith who first made me consider this aspect of the debate.

You can catch up with Jenn Smith on his YouTube channel and here Jenn Talks specifically about this issue here:

Jenn Smith: Foster Kids

Listening to Jenn Smith talk it is hard not to be concerned about an estimated figure of one in ten LAC (Looked After Children) identifing as transgender. This is contrasted with an estimated figure of one in 200 of children residing with their birth families. Another disturbing dimension is whether the indigenous children, over-represented in LAC settings, are also being medicalised as “transgender”. This has dangerous echoes of the scandal of sterilisation of indigenous peoples which is a stain on Canada’s history. If they are included in this population, of transkids, that is a damning indictment of those tasked with the welfare of children in British Columbia.

Wong does identify the dangers of social contagion in his presentation. I suspect this is now such an obvious phenomenon he feels obliged to address it. He prefaces the quotes below with some arguments that the internet has allowed “trans children” to develop an awareness of their identity and find acceptance, and knowledge, in on-line communities. Below, he at least acknowledges the dangers of kids, particularly those “on the spectrum” (referring to Autism I assume) to be swept along with trans-ideation.

Astonishingly he acknowledges that 20% of Transgender kids are autistic but this is simply dismissed because autistic kids and transgender kids are “born this way“. This is not an uncommon feature of arguments from Gender Identity proponents. Once you embrace the belief of an innate gender identity you can find evidence everywhere and fit facts to confirm your hypothesis. Conversely if, like me, you are a sceptic the ideology has more holes than a string vest.

He introduces videos throughout his presentation and one is a parent whose child came out to them at three years of age. I have not included the parent’s quote but suffice to say, like a lot of these tales, it is a boy who likes pink and sparkly things. We are told that her original therapist counselled a watch and wait approach and quoted an 80% figure for expectations of desistance. The same presentation proceeds to rubbish a study based in the Netherlands which supported this observation.

B7813443-69F4-4082-898F-6063A62BD24A

What the audience are not told is that there was only one Gender Identity clinic in the Netherlands so the researchers made the, entirely reasonable, assumption that loss to follow up could reasonably be correlated with desistance. The alternative was that the child had been taken abroad, and paid for treatment, rather than access the free treatment within the Netherlands.

Wong also rubbishes another study which found that most of the boys grew up to be gay. The unfortunately named “Sissy boys” were identified for their Gender non-conforming presentation. Here Wong argues that the study was flawed because they did not use boys who said they were actually girls. It does not seem to have occured to Wong that it was the 1970’s. Identifying as the other sex was not a social norm at the time. It is the near ubiquity of teaching about Gender Identity in our schools (especially in Canada) that has left a generation thinking you can choose your sex.

14CB146C-7A19-4130-BF3C-E0F184BD0AC0

Wong then utters this statement which shows he is utterly disregarding any research that suggests he may be making an egregious error. To much laughter he dismisses any caution with this facile statement. Apparently, if the 80% is correct he is lucky enough to be seeing the 20% who would persist. Crassly he also argues that some of those kids may not appear in the figures because they will have committed suicide. As I have said, many times, there is just no evidence for this epidemic of transgender suicides in adolescents. Wong may feel blessed and lucky but it was bad luck for any child who walked into his office.

548C0860-FB80-46C3-BD84-5545B3968623

All of which takes me to the more egregious aspect of the advice Wong is dishing out. The question of how to overcome barriers to access to Gender Identity treatment was raised. Wong requests that this part of his presentation is not taped and then, after a side swipe at the gate-keeping goverment, he advises: “Pull a stunt. Suicide, every time, they will give you what you need“

 This series is looking at the vulnerability of Children in Care; who have no parents to speak up for them.  Not all the parents in Vancover are absent.  It was also Vancouver who imprisoned a father who opposed the provision of testosterone for his  teenage daughter and refused to remain silent. It would be interesting to see who was the Gender Identity Specialist involved in that case.  Is there a connection? 

3823F6FB-DF96-4754-BE83-CD65D0CA436F

I could not say but I certainly want to do a series on parents caught up in this nightmare.

If you can support my work it will be appreciated.  Below is one way to do so until we get more media outlets willing to cover the issues I cover on my blog.  Only if it is affordable and regardless my content will remain free. 

My next piece will be on the percentage of kids in care referred to GIDs, in the U.K. Are the researchers concerned that these, vulnerable, kids have no parents to question the medical interventions proposed? Or. Are they worried children in care are not being treated fast enough? Watch this space. 

paypal.me/STILLTish

Researching Gender Identity Ideology and its impact on Women and our Gay Youth. Support is always appreciated (I have no income). All my content is open access so if you can’t speak publicly, and want to support those who can, only IF you have spare cash, this helps me keep going.

£10.00

Kiera Bell: Judicial Review

This Judicial Review was brought by Keira Bell and a parent of an autistic girl, identified as Mrs A. Applications to “intervene” in the case were brought by Mermaids, Stonewall and Transgender Trend. Only the latter were accepted by the Judges. Mermaids and Stonewall were not added to the case because the evidence they presented was not accepted, as relevant, by the by court.

You can read the full judgement here.

Bell-v-Tavistock-Judgment

5F3EEAF6-DF8B-4C66-8B82-630202331DB8

Since 2011 the Gender Identity Service , in the U.K., commonly called GIDs or The Tavistock, has been prescribing puberty lockers to children as young as 10. This was originally agreed, by the Health Regulation Authority (HRA) as a research project. The first ethics approval panel rejected the project so the Tavistock submitted to a different Ethics approval panel, who did accept it. There is a complex back story to how this experiment was launched. You can read more about this on an earlier blog:

Michael Biggs: 👇

TAVISTOCK 4 : Michael Biggs  

In this court case one of the patients from the Tavistock challenges the treatment she was given. Crucially the court considers the impact of the treatment, in both the short and long term, the evidence base for this treatment and whether these young patients can give informed consent.

One of the key issues is the lack of evidence supporting this controversial treatment. Nine years on and, by the time of this court case, the findings of this research study had still not been published! Below the Director of GIDs argued that they were about to publish the research which was too late for the Court case. Why would you not prioritise this research paper to ensure the court case had the evidence? Surely you would have expedited it if you were so certain it would support your case?

More than once the judge expresses surprise at the lack of data provided by GIDS.

Furthermore the Court, below, highlighted the dramatic rate of increase in referrals to GIDs and the change in the demographic. The lack of curiosity about this change is astounding.

It had not, however, entirely escaped the notice of GIDs. Here is Bernadette Wren, ex head of psychology at the Tavistock , speaking on this issue to the Women’s and Equalities Committee, on Transgender Equality. A social revolution that many have fought for! I wonder how many realised it would result in our young Lesbians medicalising themselves to the point of sterility? Or our gay sons retreating into faux-straight, medicalised closets? Some revolution!

The court also noted the proportion of autistic kids who are seduced by Gender Identity Ideology. This is why Mrs A is also part of this court case, her daughter is autistic. Once again the court expresses surprise at the lack of data available, from the Tavistock.

7D880695-E60A-48DB-BA14-D655CD3383CF

But the literature is available at the high number of referrals from neuro atypical children. It is so well known that Autistic charities have commented on its prevalence.

20619EDC-9ECE-407A-BA4C-9383B4D90251

Once again we see the unexpected prevalence of autistic females. 👆 Indeed it is such a well known feature that Gender Identity Ideologues like Jo Elsson-Kennedy had this to say in a, now deleted, interview. This clip is taken from a transcript of the podcast by the controversial clinic (Gender GP) run by suspended General Practitioner Helen Webberley:

DC8354FD-C4C3-4B8E-AFAF-3210410A7307

Here 👆 Olssen-Kennedy makes the extraordinary claim that symptoms of autism disappear when the Gender Dysphoria is treated.

In the full judicial transcript document the court elaborates the way Gender Dysphoria is diagnosed. I won’t reproduce here but it is a list based on how a young person deviates from sex stereotypes. I fit much of that criteria myself. How much more pronounced will Gender non-conformity be in a proto-Gay kid who may otherwise grow up as a Butch Lesbian or Femme Gay male?

These are the side effects of the treatment, Fertility and, for males, stunted genitalia high will impact on sexual function. Remember we are asking 10 year olds to sign up to this.

The Tavistock did have service users who spoke well of the Tavistock and their treatment. However these were the judges observations on the witnesses. It is extraordinary that GIDs thought their witnesses would strengthen their case.

231B9FB1-B5BF-4E62-893D-483478378F66

On the contrary a neuroscientist called into question the ability of even teenagers to consent to these treatments and highlighted the lack of impulse control which is evident before brain maturation. Notably many commentators locate brain maturation at age 25 but certainly it has not been completed by age 18! In the United Kingdom double mastectomies are available from age 17 and sexual reassignment surgery from age 18. What makes this even more alarming is that children not allowed to experience puberty may be arrested in the development of cognitive development and lag behind their peers in respect of brain maturation.

Another plank of the case was the court’s rejection of the idea that puberty blockers provide a pause for young children to be relieved from the development of sexual characteristic and time to resolve their Gender Dysphoria. The court highlights the almost inevitability of puberty blockers to be followed by cross-sex hormones. Therefore consent for one needs to encompass the cross sex hormones.

E102D165-EFAA-41B6-A076-6F599BE920D3

The full document deals with the issues of Gillick competence with reference to many other legal judgements. Many lobby groups have tried to argue this legal case throws into question rights to contraception or abortion and to smear Gender Critical arguments on this basis. This is smoke and mirrors. It is rare to find any gender critical feminists who are against the right to control fertility. We do, however, oppose the eradication of fertility in minors. This is quite a different argument.

It is worth reminding people that these children will be dependent on pharmaceutical companies for the remainder of their lives. Does #BigPharma have a vested interest in creating life long patients? Are we monetising the confusion of children, and teenagers, who have been inculcated with Gender Dysphoria by the Gender Industrial complex?

The Tavistock have won the right to appeal against the initial judgment. Mermaids and Stonewall have, once again, not been granted the right to intervene in the case. However the Endocrinology society, in the United States have been allowed to intervene as has Brook, who you may remember as a Pregnancy Advisory Service. They are now expanding their remit and cover issues around “Gender”.

You can read about Brook’s belief about “Gender” : Here

These clips should give you a clue about the stance taken by Brook. Accessed on 16th February 2021. 

289E9292-DD9D-4C6E-B884-1138C05C9F4B

As you can see they have not quite got around to updating their guidance on #PubertyBlockers. Here they describe it as merely a suspension which can be resumed if the person changes their mind. As noted above near 100% progress to Cross-Sex Hormones.

2589BD4E-336C-47A9-BB5B-55C9B9F29033

And, of course, they signpost these troubled teens to GIDs.

8FB1742C-C3C3-4D49-BCBD-BB67F01AA2C2

This incoherent ideology has captured, seemingly, all the charities operating in the U.K.  Brook would appear to be another one willing to squander its legacy in the alter of Gender Identity Ideology. 

If you are able to support my work you can do so below. 

Researching Gender Identity Ideology and its impact on Women and our Gay Youth.

£5.00

Irreversible Damage: Abigail Shrier

The Transgender Craze Seducing Our Daughters  

Shrier’s book is a timely contribution documenting increasing levels of  concern over the rising rate of Trans-identifying Females. Young girls are having drastic surgeries/medical intervention, at ever younger ages, in a quest to become their “authentic selves”. Sadly, some of those young women are emerging, in their earlier twenties, to the realisation they were simply Lesbian or in flight from their sex for other reasons.  This self-knowledge sometimes comes after years on testosterone, double mastectomies  and even hysterectomies /ovary removal. 

Facts and figures on the rising numbers of these girls are included in Shrier’s book. Many of the statistics are from the UK because the NHS makes it easier to keep track of the figures.  In the US there are now tens of “Gender Identity” clinics to service the rising rates of “transgender” children /teens. This is a phenomenon across North America, Europe and Australasia. Shrier’s book documents this  with extensive references, an excellent bibliography and conversations with many people at the cutting edge. This includes practitioners working in the field or reporting on this area.  She also shares personal testimony from the young women and their parents.

I have kept quotations to a minimum because you really should buy this book! I have, however,  interspersed some links/blogs to expand, or  reference the UK context.  

FCA2AD73-D849-4840-A4AF-48CBE346D58F

Censorship. 

When research papers, articles or books, are published on the phenomenon of Trans-identifying children/ teens, they are inevitably followed by calls to ban them, accompanied by attacks on the author, sackings, loss of office or sponsorship. This book is no different.

Here is Chase Strangio, from the ACLU (Americal Civil Liberties Union), calling Shrier’s book “dangerous polemic” and calling for it to be taken out of circulation.

863E533B-F491-42CC-8275-6EC01217F731The ACLU have a proud history defending Civil Liberties and Free Speech.  A legacy which has been utterly squandered by its advocacy of Gender Identity Ideology. As an organisation they appear  unwilling to accept that Women, LGB people and even Transsexuals,  have legitimate concerns about the extremist positions of Gender Identity Ideologues.  

Chase Strangio is a Transman and ACLU Lawyer.  Anyone questioning the transitioning of children seems to be perceived as an attack on Chase’s identity, as a man.  Choosing to critique a book without reading it seems to be common in this “debate” but  Chase claims to have actually read it.  This doesn’t  prevent Chase from seeking to deny other people the opportunity. This smacks of authoritarianism and is  shocking from an organisation which,  not too long ago, defended the right to free speech  for members of the Ku-Klux Clan.  

What is happening to Abigail’s book follows a familiar pattern of silencing. This happened to the work of Michael Bailey, Lisa Littman, Ken Zucker and many researchers whose work I have covered on this blog.

Lisa Littman

Lisa Littman coined the term “Rapid Onset Gender Dysphoria”. Lisa Littman spoke to parents with children claiming to be transgender. These children/teens had not shown any signs of discomfort, with their sex, during childhood, and their stories were also at odds with the experience / recollections of their parents. Diane Ehrensaft, a proponent of Gender Identity Ideology, made this statement about talking to parents (p.28). claiming it was akin to “recruiting from Klan or alt-right sites to demonstrate that blacks really are an inferior race”. I would contend that parents are demonised because we know when our children fabricate a fantasy trans-narrative. This knowledge is perceived as dangerous, as is (legal) parental responsibility, to safeguard our children from youthful mistakes. Parents who affirm biological sex are a direct challenge to ideologues, like Ehrensaft, who contend three year olds are competent to know their “gender identity”.

You can read more about what happened to Dr Littman here https://quillette.com/2019/03/19/an-interview-with-lisa-littman-who-coined-the-term-rapid-onset-gender-dysphoria/

You can meet Diane Ehrensaft here: https://youtu.be/DnILbwUL19Y

A tale of two sexes

Ms Shrier’s book centres teenage girls. This makes sense because young girls are emerging as the main demographic being harmed. The causes are also different for females. As a parent of one of the boys, caught up in this, I contend that, whilst there is some overlap in the causality, this is primarily a tale of two sexes. It therefore makes sense to cover boys separately. Let us hope someone takes up the challenge to look at the Transgender Craze in Our Boys. Maybe I will.

Autogynephilia

Shrier does not shy away from covering the more controversial issues accompanying Gender Identity Ideology in our society. This includes a reference to Autogynephilia (AGP) which is a male paraphilia. The love of oneself, as a woman, is the new love that cannot bear to be named. Acknowledging AGP tends to provoke narcissistic rage and backlash and explains a lot of the testeria in this “debate“.

Shrier also talks about the erosion of female only spaces (see anecdote about the bra-fiting for a teenage girl. p.143). She also covers the potential /actual destruction of female sports due to male inclusionary policies. Shrier quotes young women who told her the social cache attached to a transgender identity is in direct contrast to the disregard for Lesbians. (p.151). Why would you want to be Lesbian when it is mainly known as a category of porn? Indeed the depiction of young women, in porn generally, seems suffiicient explanation for a flight from the female sex. Looked at one way adopting a male identity is a perfectly rational response to a hostile environment.

School Policy

Shrier is also excellent on the way Transgender ideology is disseminated, particularly in schools. The same phenonemon is at play in the UK. Sometimes this is done overtly via a Transgender Policy but other times it is slipped in, covertly, under the guise of anti-bullying. To truly root it out you have to check school transgender policy but also anything referencing bullying or equality or inclusion. I am doing a series on all the policies I have found and downloaded. This is one.

School Transgender Policy 1. Brighton: Allsorts

Shrier’s also documents how parents are treated by these policies and by schools, generally.  Parents are  painted as a safeguarding risk to our children, if we don’t  immediately “affirm” a trans identity. I blogged about this here 👇 covering school policies advocating lying to parents about our children and “socially transitioning” them behind our backs. 

Putting the Loco in Loco Parentis

Another issue subject to scrutiny is the threat of suicide and the topic of transgender kids. Not just in the US but globally. This is despite the fact suicide attempts are actually no higher in trans-identifying children than other kids with mental health issues. Completed suicides are actually very rare in transgender youth but they are higher in the adult group post transition. One Swedish study, with the longest follow up time of any other study, found the suicide rate to be significantly higher than their comparator sex. You can read about this here:

https://journals.plos.org/plosone/article/file?id=10.1371/journal.pone.0016885&type=printable

2020-11-18 (2)

This is one of the longest follow up studies and points to a need for more after care and a review of the outcomes for post-operative transsexuals. This area is replete with references to suicide as evidenced by the repetition of “Better a live daughter than a dead son” . Yet discussion on post-operative mental health issues is verboten.

I wrote about suicide, in transgender youth, below.

Suicide in the Trans Community

Ray Blanchard

Shrier seems to have spoken to most of the prominent voices in this debate. Ray Blanchard is the man who coined the term Autogynephilia. He is very good on the psychological toll it takes to present as the opposite sex. I have written about this, which I call “imposter syndrome on steroids” , after observing and listening to adult transsexuals. Blanchard goes a bit “bad on both sides” re Trans Activists and Gender Critical Feminists (p. 132) but then we do appear to be, or are, critiquing his life’s work.

Medical Treatment

The book is bold and unflinching on the paucity of medical research and provides case studies on the deleterious impact of experimental, medical, solutions to a trans-identity. She points out that there is no reliable test for an innate “Gender Identity”. There is no biological marker. Detransitioners met the diagnostic criteria in the same way as did those who persist, for now, with a medicalised solution to their distress. She explodes the myth that puberty blockers are a pause and emphasises the public data which shows that 100%, put on puberty blockers, will continue to Cross Sex hormones. This is not a pause, it is the introduction to, an almost inevitable, pathway to medical transition. Shrier deals with the risks of puberty blockers (p.165); the shocking statistic of a 5 times higher rate of heart attack in females on testosterone (p. 169) and the medical complications leading to the high rate of hysterectomies after 5 years on testosterone. (p.171). She is also not afraid to name leading proponents of Gender Identity /Medical transition such as Jo Elsson-Kennedy who dismisses post mastectomy regret with this flip response “if you want breasts later on you can go and get them”. (p. 172)

Personal Testimony 

The book is packed with personal stories from parents, adult transsexuals, desisters/de-transitioners. The bulk of these are females, as you would expect, but she does also reference young males. This approach allows us to meet some of the young girls/women caught up in the Transgender phenomenon, putting flesh on the bones of the statistics, just as surely as flesh is being put on the line. We hear the voices of parents endeavouring to navigate a path to protect their children, without alienating them. This is difficult and not always successful. Young women share their stories, one on being a Butch Lesbian, who identified as trans. The anorexic who swapped pro-ana sites for transgender ones. Crucially she ends the book with stories of those who made their way back, to reconcile with their sex and, very often to their formerly estranged families. Because: There is a way back!

Cultural differences

This is clearly a global phenomenon as I have tried to demonstrate. There are also some cultural differences.  I don’t think therapy and medicalised responses to children/teenagers distress are quite as embedded in the UK.  Though I am from the North of England and we can be a bit “haven’t you got any mates?” (Crocodile Dundee Style😉)   about North American reliance on therapy. Shrier has lots to say about parenting styles and our growing impulse to step in when our children encounter difficulties. The phenomenon of Helicopter parents is less embedded in working class culture but is definitely rampant in middle class parenting.  Overall this book translates very well, to the U.K. context,  and it is eerie how much commonalty there is in the experiences of parents on both sides of the atlantic. 

In Conclusion. This is a very important book.

C21B1C31-9535-4CB2-8C0C-437A1601F1A2

Purchasing Abigail’s book via the link, below, will provide funds to a UK Parent’s group (Bayswater Support Group) who support families, with children who identify as transgender, to navigate a path to wholeness.

My copy of this book will be going to a generous donor who has purchased it to help fund my work. If you wish to support me you can do so here.

If you are able to support my work please do so. I am unwaged and all my content is open.

Investigating the march of Gender Identity Ideology. The impact on Women’s rights and the cost paid by our Gay offspring & children on the Autistic spectrum.

£10.00

Putting the Loco in Loco Parentis

The Law: In Loco Parentis

Parents  entrust our kids to the School/Teachers to look after their safety and well-being, in our stead. Forcing our girls to share mixed sex spaces, and hiding information from parents is a grave dereliction of that duty.

C54CBFDD-B299-480F-8C28-12CC7D9446397486AFF1-A723-4438-B4FE-136586AA312D

Transgender Guidance in Schools.

More and more parents have begun to raise concerns about School guidance, supposedly, developed to accommodate Transgender pupils. Grass roots organisations, such as Safe Schools Alliance, have emerged to challenge these  policies. In 2020, transgender guidance has been withdrawn in Kent, Cornwall, Shropshire, Barnsley, Warwickshire and Oxfordshire.  There are challenges underway in three further schools, of which I am aware. Thus far all the guidance has been withdrawn rather than face a legal challenge.

The Oxfordshire case is illustrative of a problematic attitude to the protected characteristic of sex.  A 13 year old girl challenged Oxfordshire County Council  via a Judicial Review. Her case aimed to gain recognition of the conflict between the protected characteristics of Sex & Gender Reassignment.  The guidance from the Department of Education argues that the protected characteristic of Gender Reassignment   covers pupils who identify as Transgender. Link to government guidance is here

Here is the relevant excerpt and look who is advising them! GIRES!

9817B132-2299-4E0E-9847-556594A248D8

This is despite the fact under 18’s cannot apply for a Gender Recognition Certificate or, legally, obtain Sexual Reassignment Surgery, in the UK.  The Transgender pupils are therefore anatomically indistinguishable from the rest of their natal sex.

415653BF-24C1-4495-8718-566771427E62

Rather than face a judicial review the council withdrew the policy. They  are clearly hoping to hide behind the skirts/trousers of the EHRC. Oxfordshire issued a statement which contained no apology, to the female pupil. Instead the Council ends with a statement about the safeguarding of its trans-identifying pupils. Nothing about a duty to safeguard, potentially vulnerable,  natal girls.

E789BCF3-ADBA-4CE1-8647-F1D2F4B336DA

C1BCF8C1-92E8-49B2-9749-3FBAF0A30F28

In this post I want to specifically focus on the way parents are regarded in these transgender toolkits.  Both the parents of children who manifest as Gender Dysphoric and the parents of other pupils.  I estimate I have looked at about twenty of these guidance packs. Below are examples of what they have to say about parents.

Most of the guidance refers to the high rate of  suicidal ideation, in our trans-identifying children. Yet the policies repeatedly state  there is no, inherent, safeguarding risk.  If our children reveal a state of gender confusion , to a member of staff, they are reminded that this is confidential  information, not to be shared, even with the child’s parents.  How can schools claim our children are at a high risk of suicide attempts and, simultaneously, state  there are no safeguarding issues. How is it  Ok to conceal this information from parents?   D7CA96FE-7B71-4AD7-B15E-78711FB533DC39310240-746C-45A5-A26D-17C3ED3F78DA

Suffolk council divides parents into the good and the bad ones.  The good ones “work alongside their child”.  Are the bad ones those who think the best outcome is a reconciliation to biological sex and not a  lifelong dependence on BigPharma?

Barnsley expresses the hope that parents will be concerned for their child’s welfare but is clearly sceptical.  At no point, in any of the policies, is there an understanding that  parents, who express caution, are the ones  acting in the best interests of our children.  Every pack I have examined is suspiciously  keen to emphasise actions the child can take independently of their parents.

5D59CE43-9CAC-4961-9C52-46EC8AB83AFC75D12F51-26FE-4E13-A40F-978E17271584

More sinister is an open statement that a school, in this case a Catholic school, can put in place a transition plan that does not involve the parents!  This is my old school and I have young relatives who attend there.

EF43C91C-8A52-4CA4-9229-4786D3A127C9


Here is another Catholic school which labels parent’s as prejudiced. It then goes on  to make the claim that Parents/Guardians may not be the most appropriate people to guide their child through transitioning!  Why is transitioning our children seen as an unmitigated good? A direct attack on parental duty of care and parental rights from the Catholic Church!.  I am an atheist but it is quite astonishing to see the undermining of Parental responsibility emanating out of Catholic schools.

8C2137E2-0B16-4F7A-8F8C-F136CADA15CFLeicestershire Council appear to see themselves as a Tavistock (Gender Identity Services) referral agent:  Actually stating here that Teachers & School Nurses, even Youth Workers are able to make referrals! 66BC6D03-BD45-465F-BEC5-54B8FE753E88

233B594E-424C-410A-8EA7-310279D9D029Where are the parents in the Leicester guidance? Once again the confidentiality of the child is placed in the foreground.  What this actually means is that the school has the right to keep secrets from the parents. Even whilst so many of these packs claim our children are at a significant risk of suicide attempts. Still it is not a safeguarding issue?

This next clip is even more disturbing.  The Leicester policy sets out a scenario where one of the parents will be actively deceived about what is going on.

F761388E-D52E-49FF-9A06-9D39780AE6E6

Of course we can all think of scenarios where parents are a risk to the safety and well-being of their child.  Why are parents, who question the uptick of girls (and boys) with Gender Dysphoria, labelled as problematic. Having navigated this territory, for my male child, I was keen that he was afforded protection but not at the expense of the female pupils.  Puberty can be a difficult time for teenage girls and they too deserve dignity, privacy and protection. Like the parent below I was able to navigate a careful path between the two protected groups.  Unlike this parent, from the Cornwall guidance, I was not faced with a Social Justice Warrior undermining these careful arrangements.

9F8A8897-F48F-4E43-B6ED-259E65F964D2The Cornwall policy was jointly drafted with a female police officer. I was surprised the statement on the left made it into the document.  Apart from a disturbing focus on links to reporting #HateCrime it was not the worst Transgender policy I read. It is, however, a, regrettably, low bar. The document also brands parents as potentially prejudiced and again argues that the child may have a perfect legal right to exclude parents from any role in preserving their healthy bodies. 1EF8DEAB-396C-4E6F-AC3F-75269D776959

You can read about the Fraser Guidelines, and Gillick Competence, mentioned above  here.   Activists  argue that transitioning children /teens against their parent’s wishes is in line with the rights of young people.  You will start to see more references to these guidelines and Gillick competence. This is intentional and designed to draw a false equivalence to access to contraception.  References will also be clothed in Human Rights speak and references to bodily autonomy. 

7BB1BE2E-9B6D-47BD-8698-646083CAB591 A lot of these guidance packs go to some lengths to make sure schools know they can honour a pupil’s preferred name and pronoun. School systems can be amended to reflect this. There is no need for a legal name change.  They also point out that, once a pupil reaches 16 they no longer need parental permission.

Shropshire also favours hiding this information from parents who are not “supportive”. I know, first hand, of parents who only discovered what was going on, with their own child, when a letter was  sent home with a new name & pronouns.  Do not tell parents can be a very dangerous message.  Some parents have children with eating disorders, psychiatric co-morbidities, and other conditions which the school may be unaware about.

CE78FE75-2E77-40EF-A11E-E7D76FF964FD

The pack which seems to be the template for most of the packs I have seen remains in operation. This is the All Sorts pack, from Brighton and Hove.  A pupil’s right to confidentiality is elevated above parental obligations, or the rights of other pupils.  Again,  because they claim it is not a safeguarding issue it can be kept from their own parents and the parents of other children.05FCA681-B055-4296-A81F-A80DB1E8C7F3

Where a parent raises a concern, about a male-bodied person in girls changing rooms, the pupil/parent’s are admonished for denying the “girlhood” of the other pupil.  In this scenario, I as a parent of a trans-identifying male, agree with the female pupil and her parent’s concerns.  I would not want my son to be exposed to the hostility, that would likely ensue, from such a stance. At the same time, if the guidance is followed, I would be totally unaware my child had formally claimed trans-status at the school. Who does this protect?  Not my son. Not the girls in his school.

2B9A333D-6B78-4879-B363-78F3F584845C

Another common feature of the Transgender Guidance is the near ubiquity of signposting to  Mermaids Charity.  This charity is a keen advocate for keeping secrets from parents.  Here is an article on their website. It  was  modified so  children could quickly exit the site and avoid their parents discovering they are seeking counsel on  Gender Identity Issues.

3596FA32-0B32-4C50-8949-CA90825E9F26

The BBC has now amended their guidance to remove signposting to Mermaids and other trans lobby groups.  I wonder how long it will take for all School guidance packs to do the same?

My Next blog will explore  this document?  Based on a project funded by the Government Equalities Office,

Here is what they have to say about parents.  This is a lie.  The Equality Act does not mandate pronouns.

EC9D9D07-0D72-4B9E-8CEE-555E91F44F80